Retatrutide receptor activity and weight loss
A molecule can activate several receptors without copying each hormone equally. The imbalance is part of the pharmacology worth understanding.
GIP, GLP-1 and glucagon receptors
Retatrutide is an engineered peptide that activates the receptors for GIP, GLP-1 and glucagon. GIP and GLP-1 help stimulate insulin release as glucose rises; the glucagon component adds a different influence on energy expenditure and fat metabolism. The review of retatrutide pharmacology and early trials explains why combining those activities became an obesity-research strategy.
Glucagon ordinarily raises blood glucose. That makes lower blood sugar during trials of the combined molecule an interesting finding, rather than a contradiction to erase. The net effect depends on the combined actions. To my ear, three identical switches would be a prettier story; the combined pharmacology has much more texture.
Unequal potency in cell assays
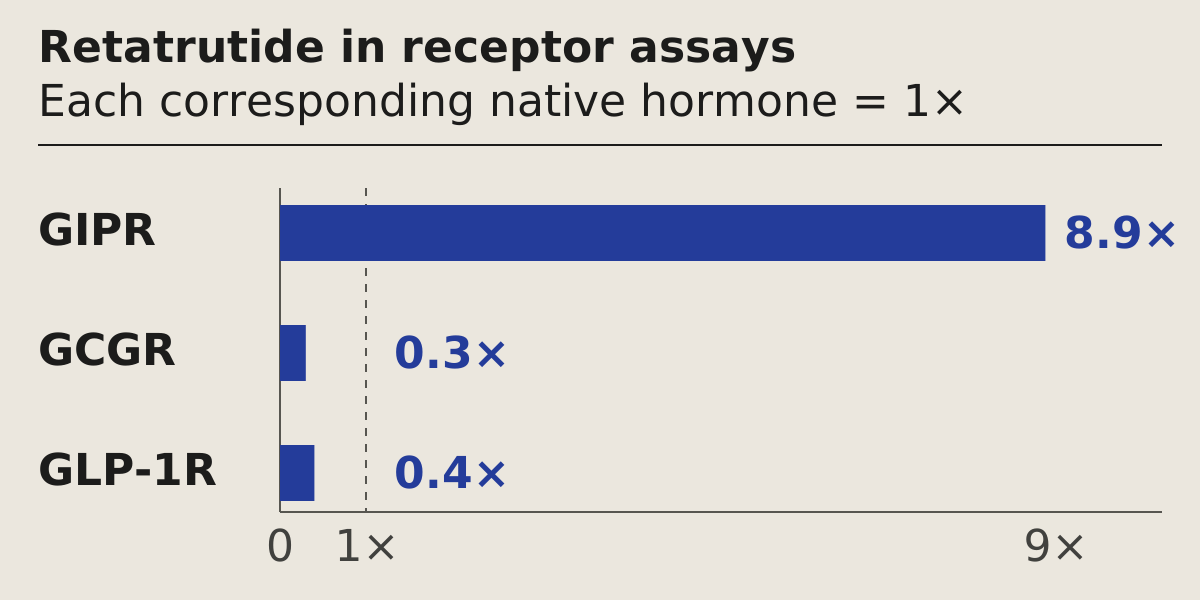
The structural and cell-signalling study examined retatrutide at all three receptors. Relative to the corresponding native hormones, potency was 8.9× at GIPR, 0.3× at GCGR and 0.4× at GLP-1R. Each comparison uses its own hormone as the reference.
These are in vitro receptor measurements. They describe a molecule's behaviour in assays, not a prediction that a person loses weight in the same proportions. I was expecting symmetry from the phrase “triple agonist”; the actual result is much more particular.
From receptor structures to clinical measurements
The same structural paper resolved retatrutide bound to each receptor using cryo-electron microscopy, an imaging method for molecular structures. It also used signalling assays and altered amino acids to investigate the interactions. A structural image explains where a molecule sits; experiments establish what changes when an interaction is altered.
I enjoy that back-and-forth between an image and a manipulation. It is a more exact question than asking whether the compound is simply stronger. A clinical outcome still has to be measured in a clinical trial.

Phase 2 outcomes
The 48-week Phase 2 obesity trial enrolled 338 adults. In the 12 mg study group, mean body-weight change was -24.2%, compared with -2.1% for placebo. Those figures describe the monitored trial group and its study dose. They provide no instructions for personal use.
A separate liver-fat substudy in participants with obesity or overweight and fatty liver disease included 98 people, without type 2 diabetes and with at least 10% liver fat at entry. In the 12 mg group, relative liver-fat change was -82.4% at 24 weeks; 86% reached the study's normal range of less than 5% liver fat. A scan crossing that threshold answers a narrower question than long-term protection from liver illness.
In 281 adults with type 2 diabetes, a separate Phase 2 trial found improved HbA1c and weight reduction. No severe hypoglycaemia was reported. The populations and follow-up periods differ, so these outcomes remain attached to their respective studies.
I consider the obesity result substantial. It deserves its exact follow-up period alongside the percentage, and the question of what happens after treatment ends remains open.
Trial tolerability
In the obesity trial, gastrointestinal adverse events were dose-related and mostly mild or moderate. Heart rate also rose in a dose-dependent pattern, peaking at 24 weeks. Longer cardiovascular and kidney outcomes and durable benefit after stopping were unresolved in this record.
Community reports describe diminished food thoughts, nausea, constipation, belching, fatigue, warmth, faster pulse and altered sleep. Some describe concern about muscle loss during rapid weight reduction. These are anecdotal accounts rather than clinical evidence; neither their product contents nor the proposed causes were established. Giving those accounts a frequency estimate would imply a kind of counting their sources cannot support.
Retatrutide remains an investigational, unapproved drug in these sources. Material obtained outside a trial has separate uncertainties about identity, strength and sterility. The trial findings cannot verify a separately obtained preparation. No approved formulation or reconstitution instructions are established here.